A woman in her 40s living in Sakuragicho, Yokohama, visited my clinic with pain in her left shoulder when raising her arm.
Approximately two weeks before visiting my clinic, she began noticing a catching or impingement-like sensation in her left shoulder when lifting her arm. At first, she noticed only a vague discomfort when putting on clothes, but the symptoms gradually became more noticeable and began causing pain at certain angles of shoulder elevation.
There was no specific injury, fall, sports activity, or other identifiable event that triggered the symptoms. She described it as pain that had simply “started without warning.”
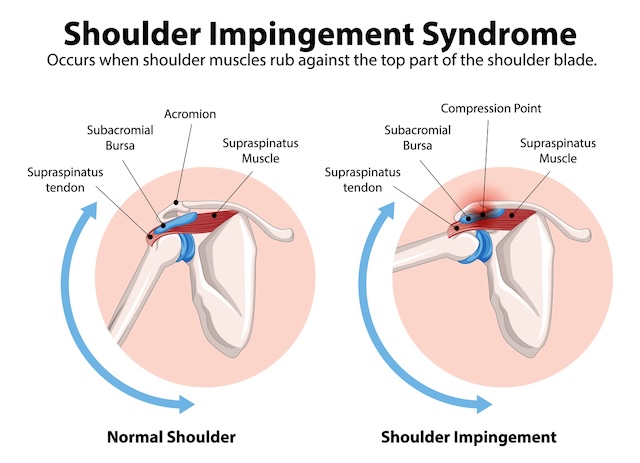
As the symptoms continued, she visited a hospital and had an X-ray examination. No obvious abnormality was found, and she was prescribed pain medication and topical patches.
However, she wanted to understand why her shoulder was painful when the X-ray showed no significant abnormality.
She had previously visited my clinic for lower back pain, which had improved with chiropractic care, so she decided to return to my clinic to have her new shoulder symptoms assessed.
Initial Examination
Medical Interview
The frequency of the pain had gradually increased.
She experienced discomfort during everyday activities such as:
- Putting on clothes
- Raising her arm to reach an overhead handrail on a train
- Lifting her left arm through a particular range of motion
Interestingly, she did not experience significant pain when simply swinging her arm back and forth.
The pain was mainly reproduced when she raised her arm through a specific range.
She was also concerned that the shoulder pain might continue to worsen if left untreated.
Visual Inspection
No obvious abnormalities were observed.
There was no visible swelling, deformity, or other notable change around the left shoulder.
Static Palpation
Light palpation of the superficial tissues revealed mild increased tension in the left deltoid.
More significant tension was noted in the rotator cuff muscles around the shoulder, including the muscles connecting the scapula to the upper arm.
Increased tension was also found in the muscles connecting the scapula to the spine on the left side.
Motion Palpation
Active Range of Motion
When the patient actively raised her left arm, pain was reproduced slightly above shoulder level, at approximately 90 degrees of elevation.
Interestingly, the pain decreased as she continued raising the arm beyond this range, and she did not experience significant pain when the arm reached full elevation.
Passive Range of Motion
When I moved her relaxed arm passively, mild discomfort was reproduced through a similar range.
However, the intensity of the pain was significantly lower than when she actively raised her arm.
Orthopedic Tests
- Painful Arc Test: Positive
- Drop Arm Test: Negative
- Codman’s Test: Positive, with pain around the supraspinatus tendon
These tests were performed to assess the possibility of shoulder impingement and involvement of the supraspinatus tendon.
I did not perform Yergason’s or Speed’s tests because these tests are primarily used to assess the biceps tendon, while the location and characteristics of her symptoms were not suggestive of primary biceps tendon involvement.
Muscle Strength Examination
I performed a strength test of the supraspinatus.
No significant weakness was observed, and the test position did not reproduce her shoulder pain.
Treatment Provided
The combination of pain during a specific range of shoulder elevation, a positive Painful Arc Test and Codman’s Test, and increased muscle tension around the shoulder was considered consistent with shoulder impingement-type symptoms involving the supraspinatus region.
Her X-ray had not shown any obvious structural abnormality, and there was no apparent weakness of the supraspinatus.
Based on these findings, I focused on the relationship between the shoulder joint, scapular movement, and the surrounding muscles rather than treating only the painful area.
Muscle Treatment
My main focus was to improve the movement of the scapula and shoulder by addressing excessive muscle tension around the shoulder complex.
I worked on the following muscles:
- Supraspinatus
- Infraspinatus
- Subscapularis
- Teres minor
- Rhomboids
- Levator scapulae
- Pectoralis major and minor
- Deltoid
- Biceps
- Triceps
These muscles all contribute to shoulder and arm movement. I therefore aimed to reduce excessive muscle tension and improve the way the shoulder and scapula moved together.
Joint Treatment
I found that the left shoulder tended toward internal rotation, which I considered potentially relevant to the way the shoulder moved during elevation.
I therefore performed a joint mobilization technique to encourage improved external rotation of the shoulder.
I also assessed the movement of the left fifth and sixth ribs and performed an adjustment to address the restricted movement found in this area.
After treatment, I asked her to raise her left arm again.
The pain that had previously been reproduced during shoulder elevation was noticeably reduced.
Because her work schedule only allowed her to visit on weekends, I recommended a follow-up appointment one week later.
Treatment Progress
Second Visit
When she returned one week later, most of the shoulder pain had already disappeared.
She had not experienced any significant recurrence of pain during the week following the initial treatment.
I repeated the assessment and continued with a similar treatment approach for the shoulder and surrounding muscles and joints.
Because I had previously treated her for lower back pain, I also assessed and treated her lower back as part of a broader approach to her overall musculoskeletal condition.
I recommended another visit two weeks later to monitor her progress.
Third Visit
She returned two weeks later and reported that the left shoulder pain had completely resolved.
She was able to move her shoulder normally during her daily activities without experiencing the previous pain.
As the original shoulder symptoms had resolved, I concluded the treatment for this particular complaint.
At her request, she subsequently began regular monthly maintenance sessions focusing on her overall musculoskeletal condition.
She has continued these monthly visits for approximately two years.
Practitioner’s Opinion
This case presented with several findings consistent with shoulder impingement-type symptoms, including pain during a specific range of shoulder elevation, a positive Painful Arc Test, a positive Codman’s Test, and increased tension in the muscles surrounding the shoulder and scapula.
At the same time, the patient did not have significant weakness of the supraspinatus, and her X-ray did not show an obvious structural abnormality.
For this reason, I considered it important to look beyond the painful area itself and assess how the shoulder joint, scapula, and surrounding muscles were functioning together.
Rather than assuming that the supraspinatus tendon itself was the only source of the symptoms, I considered the mechanical loading and movement of the entire shoulder complex.
The patient reported a substantial reduction in pain after the initial treatment, and most of the symptoms had disappeared by the second visit. By the third visit, she reported that the pain had completely resolved.
However, this does not mean that every case of shoulder impingement will improve within the same number of visits. The required treatment and recovery time can vary depending on the duration and severity of symptoms, the condition of the shoulder, activity level, and other individual factors.
This case also highlights why I believe it is important to assess shoulder movement, scapular function, and the surrounding muscles, rather than focusing solely on the location where the patient feels pain.
If you experience shoulder pain when raising your arm, pain when reaching overhead, pain when putting on clothes, or shoulder pain that occurs within a specific range of motion, a detailed assessment can help identify factors that may be contributing to the symptoms.
Shoulder Pain and Chiropractic Care in Yokohama
My goal is not simply to provide temporary symptom relief, but to identify the underlying factors contributing to your condition, improve joint function and movement, and help reduce the risk of recurrence through individualized chiropractic care.
My clinic, Spine Chiropractic, is conveniently located in the heart of Yokohama, just 1 minute from Bashamichi Station, 7 minutes from JR Kannai Station, 8 minutes from Nihon-Odori Station, and 12 minutes from JR Sakuragicho Station.
I welcome both local residents and international patients, providing chiropractic care in both English and Japanese.
If you are searching for an English-speaking chiropractor in Yokohama for shoulder pain, shoulder impingement, or pain when raising your arm, I provide a detailed assessment and personalized chiropractic care based on your individual symptoms and physical findings.
Whether you live or work around Bashamichi, Kannai, Sakuragicho, Minato Mirai, or Nihon-Odori, my clinic is easily accessible for people looking for chiropractic care for shoulder pain and other musculoskeletal conditions.
At Spine Chiropractic, I address a wide range of musculoskeletal conditions directly impacting daily life, not merely as a form of relaxation therapy. Conveniently located within a one-minute walk from Bashamichi Station, an eight-minute walk from Nihon-Odori Station, a seven-minute walk from JR Kannai Station, and a 12-minute walk from JR Sakuragicho Station, my clinic is well-suited for residents and workers in the Yokohama area.
If you are experiencing similar symptoms, please feel free to visit Spine Chiropractic. I am committed to providing care with sincerity and professionalism.